

The Arts serve as a Positive Psychological Intervention (PPI) and contribute to subjective and psychological wellbeing.
Image Credit: Chicago : Illinois WPA Art Project, [between 1936 and 1940]. Library of Congress.
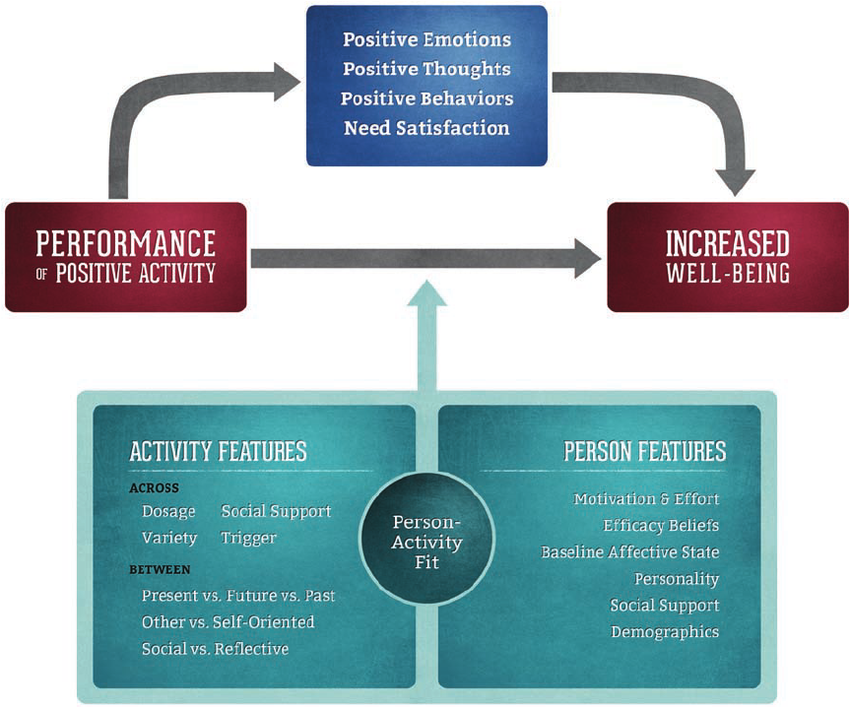
Positive Activity Model
Person-Activity Fit
How Do Simple Positive Activities Increase Well-Being?
Credit: Sonja Lyubomirsky, Ph.D. and Kristin Layous, Ph.D.
Wellbeing is a Public Health Issue
By, Virginia Valerio Lambert, September 23, 2023
Abstract
Well-being interventions are an important tool in helping populations cultivate positive feelings,
behaviors, or thoughts. More importantly, identifying those that work well and for whom is
equally important. Our paper builds on Heintzelman et al. (2023). We randomly assigned people
to work on PPIs that were either matched to their strengths, matched their weaknesses, or self-
selected. We assessed well-being before and after a 4-week PPIs and again three to four weeks
later. This endeavor involved Prolific Academic, an online platform widely used by researchers
interested in working with public participants. The survey was advertised as “Person-Activity Fit
for Online Happiness Practices”. As predicted, out to post-intervention, the weaknesses condition
improved in well-being significantly more than the strengths condition. Likewise, the self-
selection condition improved in well-being significantly more than the strengths condition out to
post-intervention. Additionally, the weaknesses and self-selection conditions did not have
significantly different trajectories of well-being from the strengths condition out to follow-up.
The desire for well-being is a universal one. It’s a topic discussed in legislative chambers,
academia, and amongst healthcare professionals. Given this knowledge, how well are we
identifying what contributes to well-being, source interventions designed to improve well-being,
and more importantly, of those identified, how effective are they at generalizing to the public.
For this study well-being constitutes two approaches, subjective well-being (SWB) and
psychological well-being (PWB). The two inform positive psychological interventions (PPIs)
either independent of each other or in this study’s case, together as well. The SWB model can be
explained as traits such as cheerful disposition that may help mitigate negative life experiences.
The PWB model is understood to involve personal growth measures such as personal growth.
The Koydemir et al. (2021) study identified interventions that target both SWB and PWB
together as showing greater promise evidenced by the effect size and sustained long term
temporal benefits exhibited in adult participants. Their results substantiate the claim that PPIs
improve well-being. Nevertheless, there are limitations and suggestions to consider. There are
three additional points to touch on for future research, that of reliability, validity, and to consider
measures other than self-report methods (Koydemir et al., 2021). Additionally, to address the
three, socioeconomic status (SES) should be a consideration as it possibly mitigates the self-
report concern as well as provide an opportunity to generalize to the greater population, which is
a prerequisite for validity.
We witness individuals with means accessing resources to help them address concerns
that have contributed to a less than optimum mental and physical well-being. Then you have
those who do not have the means to access the same resources. Additionally, with the notion that
research is conducted to drill down on issues in the hope of informing stakeholders interested in
either ensuring well-being or methods designed to mitigate poor well-being, the research being
conducted when dealing with the topic of public health must have internal and external validity.
Therefore, it is imperative that socio-economic status (SES) factors are considered. Efforts to
mitigate factors or variables that are a hindrance to well-being are devised and measured to
gauge efficacy in the hopes of deploying to the general at large.
Efficacy of PPIs
From research conducted under the Positive Psychology discipline, a Meta-Analysis
study involving 68 randomized controlled peer-reviewed studies tested the effect of PPIs versus
control on Subjective Well-Being (SWB) and Psychological Well-Being (PWB) examining for
efficacy in measuring SWB and PWB or a combination of both measures (Koydemir et al.,
2021). The present study cast a wide net by incorporating an analysis of past studies, focusing on
Well-Being, Duration of Intervention and length of Sessions, Age, and Delivery Method (online
or traditional). As the study sought to make use of past and recent experimental research, they
made use of four online databases which garnered 223 studies with 16,085 participants, resulting
with findings of where participants fell in regard to SWB and PWB. The results of this study
indicated that PPIs effectively increased SWB and PWB over control groups. Their analysis
showed that interventions on a short-term (3 months) and long-term (6-months) approach
favored long term, especially when it came to older participants. Whereas younger participants
benefitted better from short term interventions. Additionally, participants generally benefited
more when interventions were a combination of both PWB and SWB. When considering the
Koydemir et al. (2021) paper in comparison to the Heintzelman et al. (2023) paper, there are
different measurements to consider. The Heintzelman et al. (2023) paper has a Positive
Engagement Model, Medical Model, Strengths-Based Model, and Autonomy Model.
The significant difference between the two is that the Koydemir et al. (2021) study does not
incorporate clinical (Medical Model). Nevertheless, the overarching research is similar. They are
both attempting to show which approaches or measures work best to help participants achieve
well-being.
Person Activity Fit
Heintzelman et al. (2023) explain person activity fit as an optimal match between an
activity and the individual performing it. Bearing in mind individual character traits and trusting
a participant to choose activities that meet their needs, this approach helps ensure participants
experience greater success when affording a degree of autonomy.
Strategies
As for strategies employed, Heintzelman et al. (2023) primary goal was to test the
efficacy of different PPIs personalization strategies for improving well-being. In one experiment,
participants were randomly assigned to one of three positive intervention conditions manipulated
to assess different types of person-activity fit (Heintzelman et al., 2023). In the first condition,
participants were assigned to work on five (out of ten possible) happiness skills that addressed
their weaknesses. In the second condition, participants self-selected their targeted happiness
skills (again, five out of ten). Finally, in the third condition, participants were randomly assigned
to complete five out of ten possible happiness skills. All participants focused on one happiness
skill per week for five weeks and then had five weeks of booster material for their topics. Before
and after the 10-week intervention, participants reported their life satisfaction, positive affect,
and negative affect. Participants in the self-selection condition decreased in negative affect to a
greater extent than the random condition but did not increase more in positive affect.
Alternatively, participants in the weaknesses condition increased in positive affect to a greater
extent than the random condition but did not decrease more in negative affect. There were no
significant condition differences on changes in life satisfaction. These data demonstrate that
personalization of positive interventions (i.e., weaknesses and self-selection conditions) can
show greater improvements in well-being than random approaches. Our experiment will build on
this work by once again testing the efficacy of the weaknesses and self-selection conditions to
improve well-being, and also exploring how assigning participants to work on their strengths
compares to the weaknesses and self-selection approaches.
Strengths Focus
Research by Gander et al. (2013) conducted a strength-based intervention and found that
such interventions can enhance happiness. Gander et al. also emerged with the questions of
whether personality factors should be considered and whether interventions should be
personalized. Finally, the Centers for Disease Control and Prevention (CDC) defines public
health as promoting, improving, and protecting the health of our society through making healthy
lifestyles more accessible, epidemiological research, and infectious disease control (Darrow,
2015). As numerous studies above have alluded to, there is a concerted effort to better
understand previous interventions, participants’ diversity, methods, and outcome. This is in large
part because a nation’s health and productivity are a reflection of the collective subjective and
psychological health of the population. Therefore, a national concern and public health issue.
The Significance of Socioeconomic Status
The article written by Barger et al. (2009) conducted a multivariate analysis utilizing data
from two previous national surveys involving approximately 330,247 American participants
combined. The research investigated life satisfaction disparities for White, Black, and Hispanic
respondents and assessed the relative contributions of socio-economic status (SES), health status,
and social relationships to said disparities. Barger et al. (2009) found that Black and Hispanic
respondents, as compared to their White counterparts, were less likely to report being very
satisfied and Black respondents were more likely to report being dissatisfied. Controlling for
SES and health status explained some of the discrepancy between White and Black participants
on life satisfaction and explained all of the difference between Hispanic and White participants
in life satisfaction. The purpose of this research was to better understand the underlying reasons
for well-being, and associated disparities, amongst Americans of various racial/ethnic identities
as this may help policy makers better understand how the nation is doing under the public health
umbrella, identify themes, and develop interventions to mitigate issues. To do so on a
comprehensive level, research needs to incorporate all racial and ethnic populations and factors
that contribute to better life outcomes as well as hindrances, and to what extent the two outcomes
inform education choices, which is a determinant for employment and health, for example. As
Barger et al. (2009) make note of the need for subsequent research to be inclusive and
incorporate SES into its measures. This is further alluded to in the Gander et al. (2013) paper as
they refer to the need for societal epidemiological mitigation measures.
The Current Study
Participants were randomly assigned to work on PPIs that were matched to experimental
conditions strengths, weaknesses, or self-selected conditions. We assessed well-being on a post
intervention and follow-up timetable, before and after a 4-week PPIs and again three to four
weeks later. I predict that the weaknesses condition will report higher well-being at post-
intervention and follow-up than the strengths condition. As previously reported in the
Heintzelman et al. (2022) paper, participants who were able to choose self-selection, they were
more likely to opt for weakness-based activities. The belief is that participants would be more
likely to commit to a weakness of their choosing. Additionally, I predict that the self-selection
condition will report similar well-being at post-intervention and follow-up than the strengths
condition as Self-selection equates to autonomy. Participants who feel empowered are likely to
be more motivated. As previously mentioned, authors have advised to include a broader, more
representative sample, considering the potential benefits said interventions may offer society as a
whole. Thus, my additional hypothesis involves socioeconomic status. If SES is accounted for in
the creation of a positive psychology intervention it will increase the efficacy of said
interventions for participants. Between-condition studies involve an individual and a specific
condition. SES is individual based. By isolating the participant and their associated SES
specifics, the resulting outcomes can serve as a model applicable to them as well as those within
similar parameters. This hypothesis is supported by previous analysis that showed that 6-9% of
the variance seen in life satisfaction is accounted for by SES. Furthermore, as the Gander et al.
(2013) study suggests, strengths should be included as a moderator. SES in itself is an
informative moderator as well as resilience. Due to this, it is important to consider whether PPIs
are more effective among those of lower SES who may need support for their well-being. In
addition, it is important to consider whether PPIs that have historically excluded SES, generalize
to this population.
Participants
Participants from the United States (N = 850) were recruited from Prolific Academic
(https://www.prolific.com/) an online platform that provides researchers with a means of
working with interested participants while conducting research. The study was advertised as
“Person-Activity Fit for Online Happiness Practices”. Participants were financially compensated
for their time spanning six stages of the study, incrementally beginning at $3.00, $3.25, $3.50,
$3.75, $4.00, and $4.25, resulting in a total compensation of $21.75 if all parts were completed.
Participants ages ranged from 18 to 81 years (M = 38.86, SD = 12.80), and 52.54% of the sample
identified as Male, with 45.53% identifying as Female, 1.65% identifying as Nonbinary, 0.35%
of the sample Prefer not to state, 0.71% Middle Eastern, 0.59% Native American, 0.12%
Hawaiian/Pacific Islander, 0.12% as Other. Socioeconomic status was measured on a 7-point
scale (1 = very bottom, 7 = very top) asking participants to compare their status to others (M =
3.79, SD = 1.17).
Measures and Procedure
We advertised our six-part study as “Person-Activity Fit for Online Happiness Practices”
and interested participants from Prolific Academic signed up for the study and provided consent
before completing any measures. We told all participants that they would be engaging in
research-tested ways to increase their happiness, but that they would be assigned happiness
practices with different matching strategies so we could test hypotheses about person-activity fit.
All aspects of the study were completed online via Qualtrics.
First, participants completed various measures indicating the degree to which they
exhibited various character virtues (e.g., gratitude, mindfulness, resilience). Next, participants
were randomly assigned to one of three conditions: strengths (n = 285), weaknesses (n = 279), or
self-selection (n = 280). Participants in the strengths and weaknesses conditions then ranked five
of the character virtues (gratitude, mindfulness, empathy, social connection, and resilience)
according to which one was their strongest to which one was their least strong attribute.
Alternatively, participants in the self-selection condition ranked these same five virtues
according to which one they would most to least want to practice. Regardless of condition,
every participant was assigned to work on one happiness practice per week for four weeks.
Participants were matched to their happiness practice according to their condition and their
responses to the ranking questions. Specifically, participants in the strengths condition were
assigned to work on happiness practices that matched their top-ranked virtue. For example, if
they ranked gratitude as their top virtue, they would be assigned to weekly activities that practiced
gratitude (Gratitude Journal, Gratitude Letter, Gratitude Meditation, and Three Good Things).
Participants in the weaknesses condition wereassigned to work on happiness practices that matched
their bottom-ranked virtue. Lastly, participants in the self-selection condition were assigned to work on
the virtue that they indicated they would most want to practice (their top ranked virtue).
Before being assigned a happiness practice for the first week, participants reported their
well-being with three items, “I feel satisfied with my life.” “I have a sense of meaning and
purpose in my life,” and “I generally feel happy,” on a 5-point scale (Not at all, Slightly,
Somewhat, Mostly, and Completely). These items were consistent with one another, so we
averaged them into a baseline well-being composite (Cronbach’s ⍺ = .91, M = 3.26, SD =
1.09).
Next, participants were assigned their first happiness practice for the week according to
their condition and virtue rankings. The following week, participants were invited to take part in
the second time point in which they completed weekly well-being measures (not used in the
current study) and were assigned their second happiness practice. Participants were invited
in the same way to take part in the third and fourth time points in which they received their
third and fourth happiness practices. One week after their fourth happiness practice instructions,
participants were invited back to complete post-intervention measures.
Specifically, they once again report their well-being with the previously mentioned three-
item composite (Cronbach’s ⍺ = .94, M = 3.38, SD = 1.08). Three to four weeks later,
participants reported their well-being once more to assess the longevity of the effects
(Cronbach’s ⍺ = .94, M = 3.42, SD = 1.06). Finally, participants answered open-ended questions
about their experience in the study and were debriefed as to the purpose of the study.
Results
First, we analyzed changes in well-being from baseline to post-intervention and from
baseline to follow-up with paired samples t-tests across the entire samples. We found significant
changes in well-being out to post-intervention, t(807) = 5.94, p < .001, d = .21, 95% CI [0.14,
0.28], and follow-up, t(783) = 7.71, p < .001, d = .28, 95% CI [0.20, 0.35].
To address our between-condition hypothesis, we conducted linear regression analysis
with post-intervention or follow-up well-being as the dependent variables and centered baseline
well-being and dummy-coded condition variables as the predictors (see Table 1). Specifically,
the strengths condition was the reference group (0), and we entered the weakness and self-
selection conditions as dummy-coded (1) predictor variables.
As predicted, out to post-intervention, the weaknesses condition improved in well-being
significantly more than the strengths condition. Contrary to my prediction, the self-selection
condition was not similar in well-being. In addition, as predicted, the weaknesses and self-
selection conditions did not have significantly different trajectories of well-being from the
strengths condition out to follow-up.
Additionally, we conducted an exploratory analysis incorporating socioeconomic status
(SES) in the model to explore the degree to which SES related to changes in well-being in each
condition (Figure 1). This graph depicts the model-predicted post-intervention well-being by
condition and level of SES, controlling for pre-intervention well-being. Specifically, in the linear
regression model, we added centered SES to the model to explore the effect of SES in the
strengths condition, and we also added interaction terms to explore whether the effect of SES
was different in the weaknesses condition or self-selection condition then it was in the strengths
condition.
The between-condition differences on post-intervention well-being that we documented
remained, but we also found SES to moderate the effects. First, as indicated by our centered SES
parameter estimate, higher SES predicted higher gains in well-being out to post-intervention in
the strengths condition, b = 0.076, SE = 0.031, 95% CI [0.015, 0.138], t(807) = 2.427 p = 0.015.
The Weakness X SES interaction term was not significant, indicating that higher SES was also
predictive of higher well-being gains in the weakness condition (as it was in the strengths
condition), b = -0.024, SE = 0.042, 95% CI [-0.106, 0.058], t(807) = -0.573, p = 0.566. Finally,
the Self-selection X SES interaction term was significant; whereas higher SES was associated
with larger gains in well-being in the strengths condition, it was not in the self-selection
condition, b = -0.075, SE = 0.041, 95% CI [-0.155, 0.006], t(807) = -1.825 p = 0.068. A plot of
the model-predicted post-intervention means demonstrates that participants in the self-selection
condition had higher well-being than those in the other conditions across levels of SES and the
line is relatively flat indicating that post-intervention well-being was consistent across levels of
SES in the self-selection condition (Figure 1). The significant post-intervention SES effects were
no longer significant at follow-up well-being.
Discussion
Weakness and self-selection conditions both significantly increased in well-being in pre-
to post- intervention more than the strengths condition. Both weakness and self-selection
conditions no longer had statistically significantly higher increases than the strengths condition at
follow-up. Self-selection is predicting higher levels of post-intervention well-being across levels
of SES. The weaknesses condition was less effective than self-selection and actually worked
better for those with relatively higher SES. Similarly, the strengths condition was less effective
than the self-selection condition and actually worked better for those with relatively higher SES.
Figure 1 clearly demonstrates that among those who self-selected their PPIs, SES did not really
matter for them. There were good effects witnessed across SES levels. Whereas for the strengths
and weaknesses conditions, higher SES was helpful.
The self-selection condition is equally effective across SES. Our main condition findings
were that weaknesses and self-selection remained the same. However, we did find effects of
SES. Those in higher SES benefited more from the strength condition as opposed to lower in
SES. This was also the case for the weaknesses condition as it was not significantly different
from the strengths condition. For the SES and self-select, there was no effect in the self-select
condition. It was equally effective across SES levels. Upon running a linear regression
incorporating SES, C_SES indicates b = 0.076, SE = 0.031, 95% CI [0.015, 0.138], t(807) =
2.427 p = 0.015. SESXWE indicates b = -0.024, SE = 0.042, 95% CI [-0.106, 0.058], t(807) = –
0.573, p = 0.566. SESXSS indicates b = -0.075, SE = 0.041, 95% CI [-0.155, 0.006], t(807) = –
1.825 p = 0.068. As predicted, the weaknesses condition out to post-intervention, the weaknesses
condition improved in well-being significantly more than the strengths condition. Likewise, the
self-selection condition improved in well-being significantly more than the strengths condition
out to post-intervention. In addition, as predicted, the weaknesses and self-selection conditions
did not have significantly different trajectories of well-being from the strengths condition out to
follow-up.
The Heintzelman et al. (2023) study was able to show potential when “personalizing PPIs
activities” for participants, regardless of “self-select or weakness-based assignments” (p13). The
most significant statistical findings were with negative affect from baseline to post-test.
Limitations and Future Directions
As for limitations, because our participants originated from an online platform, the
assumption is that participants have internet access and are familiar with online surveys. There is
a distinct possibility that certain participants from lower SES backgrounds would be excluded,
resulting in external validity issues. Secondly, as the participant population was
disproportionately White, this poses a problem for generalizability. The last limitation to
consider would be a control group. This study lacked a neutral control group, as its conditions
were all happiness interventions. Control groups are important when conducting experiments.
When considering future directions, crowdsourcing research work by multiple labs would
increase the number of participants. As the paper alludes to, well-being is a global issue. With
that, comes cultural sensitivities. If you were to approach this research on a global scale, the PPIs
would need to ensure you measure for collectivist versus individualist values. Another
consideration would be open-ended questions about participants’ greatest weaknesses in regard
to their happiness and then ask them to work on that weakness. Additionally, as these
interventions are intended to gauge effectiveness of activities that lend themselves to greater
happiness, this is a universal one in which SES needs to be incorporated as well as randomized
amongst a broader more inclusive population. Lastly, a limitation and possible future direction
would be to capture individual participant differences. Resilience is considered a trait that typically
helps people better tackle and cope with issues in life and may very well aid in tackling
PPIs challenges.
Conclusion
From the numerous reports cited it is apparent that Positive Psychological Interventions
(PPIs) work, but consideration must be given to the personalization factor. Self-selection of
happiness activities was effective across all levels of SES whereas working on strengths and
weakness were less effective among those with lower SES. Given the importance of PPIs for the
improvement of individual well-being, it is important to account for the benefit of personalizing
the intervention to the needs of the person in favor of other approaches, particularly those that
have been proven ineffective for a given certain SES.
References
Barger, S. D., Donoho, C. J., & Wayment, H. A. (2009). The relative contributions of
race/ethnicity, socioeconomic status, health, and social relationships to life satisfaction in
the United States. Quality of Life Research, 18(2), 179-89.
https://doi.org/10.1007/s11136-008-9426-2
Darrow, W. W. (2015). The Decline and disorganization of public health in the United States.
International Journal of Social Quality, 5(2), 29–45.
https://doi.org/10.3167/IJSQ.2015.050203
Gander, F., Proyer, R., Ruch, W., & Wyss, T. (2013). Strength-based positive interventions:
further evidence for their potential in enhancing well-being and alleviating depression.
Journal of Happiness Studies, 14(4), 1241–1259. https://doi.org/10.1007/s10902-012-
9380-0
Heintzelman, S. J., Kushlev, K., & Diener, E. (2023). Personalizing a positive psychology
intervention improves well-being. Applied Psychology: Health and Well-Being, 1-22.
https://doi.org/10.1111/aphw.12436
Koydemir, S., Sökmez, A. B., & Schütz, A. (2021). A meta-analysis of the effectiveness of
randomized controlled positive psychological interventions on subjective and
psychological well-being. Applied Research in Quality of Life, 16, 1145–1185.